Tuesday, October 28, 2014

October 28, 2014 Grand Rounds

Case # 1. A 46/M with Burkitt's lymphoma, treatment-related myelodysplastic syndrome, s/p allogeneic stem cell transplantation 11 months prior to admission, who p/w intractable complex partial seizure and fever secondary to HHV-6 encephalitis

https://www.google.com/search?q=HHV-6&source=lnms&tbm=isch&sa=X&ei=natPVLyEMouvyQSZnYEo&ved=0CAkQ_AUoAg&biw=1920&bih=943#facrc=_&imgdii=_&imgrc=FqMPqQ62M74lAM%253A%3B9mqEToEvcY-DhM%3Bhttp%253A%252F%252Fupload.wikimedia.org%252Fwikipedia%252Fcommons%252Fc%252Fc8%252FHHV-6_inclusion_bodies.jpg%3Bhttp%253A%252F%252Fen.wikipedia.org%252Fwiki%252FHuman_herpesvirus_6%3B1350%3B900

1. The most consistently reported syndrome associated with HHV-6 infection among transplant patients is encephalitis. Patients can have mental status changes, behavioral disturbance, memory loss, and seizures. Other manifestations of HHV-6 in this patient population include: fever and rash, hepatitis, gastro-duodenitis, colitis, pneumonitis, and encephalitis.

2. A positive HHV-6 PCR from tissues can suggest the presence of disease. However, there is no single test that can differentiate HHV-6 causing disease from HHV-6 that is genomically integrated. A persistently high titer of HHV-6 PCR from tissues suggests genomically integrated HHV-6.

3. One study mentioned that even in asymptomatic transplant patients, HHV-6 can be detected in the CSF.

4. Treatment involves use of either ganciclovir, foscarnet, or cidofovir. There are no randomized controlled trials on antiviral efficacy. Reduction of a patient's immunosuppression is also recommended.Read here for more information.

Case # 2. A 31-day old infant presents with fever, rash, seizure, abdominal distension, and respiratory failure secondary to human parechovirus (HPeV) infection.

1. In an infant who presents with sepsis and CNS symptoms and the CSF is normal, think about HPeV infection. In one case series, CSF abnormalities in patients with HPeV infection were rare.

2. In adults, HPeV can present as fever, myalgia, and pharyngitis.

3. More on HPeV infection from blog entry dated July 22, 2014.

Tuesday, October 14, 2014

October 14, 2014 Grand Rounds

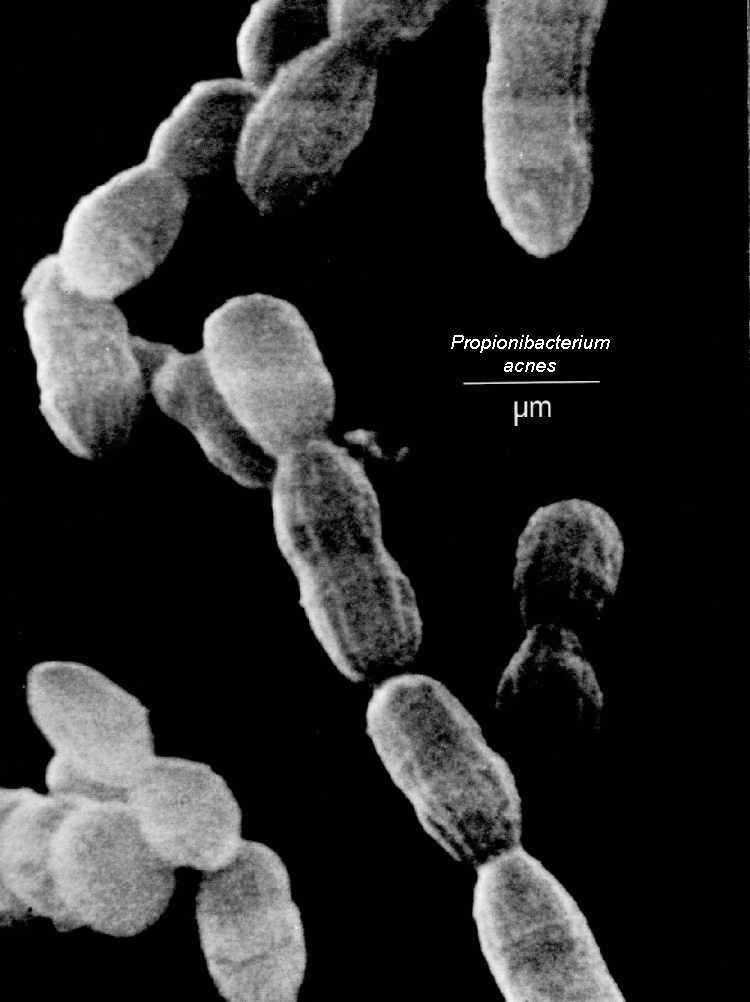
Case 1. A 43/M with CML s/p stem cell transplantation 2 years ago who p/w a 1.5 year h/o chronic lymphocytic meningitis associated with obstructive hydrocephalus secondary to chronic CNS Propionebacterium acne infection

 
 Taken from: http://luskiewnik.strefa.pl/acne/propionibacterium_acnes_files/propioni.jpeg

1. Propionebacterium acne has been shown in case reports and case series to cause chronic meningitis even in patients with no history of neurosurgical procedure (read here). It is seen in both immunocompromised and immunocompetent individuals. In most cases, a mononuclear-predominant pleocytosis is appreciated from the CSF.

2. Another learning point is that, the diagnosis of Propionebacterium acne chronic meningitis in this case was aided by the use of next generation sequencing (which maybe more sensitive that 16S rRNA gene sequencing). Read here regarding the NEJM article that chronicles how a patient with chronic neuroleptospirosis was diagnosed by this method.

Case 2. A 15-month old child with cartilage-hair hypoplasia syndrome (associated with severe combined immunodeficiency) presents with persistent diarrhea secondary to Norovirus infection

 Taken from: http://upload.wikimedia.org/wikipedia/commons/a/ae/Norovirus_4.jpg

1. Norovirus infection is self-limited and typically lasts for 2-3 days. However, in immunocompromised patients, the diarrhea can persist for several weeks to months and is sometimes associated with substantial symptoms that include severe debilitation and weight loss. It should be added in the differential diagnoses of immunocompromised patients with chronic diarrhea that eludes diagnosis. Further readings here and here.

2. Norovirus is diagnosed with stool PCR. There is no specific treatment for infection apart from supportive care. In immunocompromised patients, reduction of immunosuppression may help. Good evidence with the use of enteral immunoglobulins, nitazoxanide, and ribavirin is lacking at present.

Case 3.  A 68/F with cochlear implants presents with Streptococcus pneumoniae meningitis, pneumonia, and endocarditis (the Austrian triad/syndrome)

1. One needs to rule out endocarditis with a TEE in a patient with co-occurrence of pneumococcal meningitis and pneumonia. At least 2/3 of patients with pneumococcal endocarditis have concurrent pneumococcal pneumonia and meningitis.

2. Patients who develop acute otitis media after cochlear implantation have the greatest risk of subsequent pneumococcal meningitis. Most common organisms isolated are Streptococcus pneumoniae, Haemophilus influenzae, Streptococcus pyogenes, Branhamella catarrhalis, Staphylococcus aureus, mixed organisms, and gram negative bacilli.

3. Patients with cochlear implants and immunocompromising conditions (and recently, patients at least 65 years, read here) should get 13-valent pneumococcal conjugate vaccine on top of 23-valent pneumococcal polysaccharide vaccine.

Tuesday, September 16, 2014

September 16, 2014 Grand Rounds

Case # 1. A 54/M with chronic malaise, low back pain and new-onset heart failure secondary to subacute infected endocarditis (IE) secondary to Abiotrophia defectiva.

Taken from: http://medicine.creighton.edu/medschool/WebAtlas/secure/id/strep1/images/Strep%20NDS.jpg

1. Abiotrophia defectiva and Granulicatella sp are nutritionally-variant Streptococcus (NVS) that require pyridoxal for growth on culture. They are part of the normal oral, gastrointestinal, upper respiratory and urogenital flora. They are known to cause IE but they can also lead to primary bacteremia in patients with hematologic malignancy.

2. Compared with IE caused by viridans group Streptococcus, IE associated with NVS is usually characterized by smaller vegetation but with greater incidence of septic embolization. It also carries higher failure, relapse, and mortality rates. 

3. IE associated with NVS is treated with ampicillin and gentamicin (or vancomycin plus gentamicin for penicillin-allergic patients) similar to Enterococcus-associated IE. 

4. Abiotrophia defectiva shows in vitro susceptibility to vancomycin, rifampin, clindamycin, chloramphenicol, erythromycin, and levofloxacin. On the other hand, Granulicatella sp. are more likely to be resistant to penicillin and cephalosporins compared with Abiotrophia.


Case # 2. An 18/M with h/o bilateral lung transplantation for idiopathic bronchiolitis obliterans 2 years ago and poorly adherent to prednisone, tacrolimus, mycophenolate, and atovaquone presented with acute and progressive respiratory failure secondary to acute rejection; respiratory multiplex PCR tested positive for rhinovirus/enterovirus.

1. From last week's discussion, we know that the detection of rhinovirus/enterovirus using the multiplex PCR test is a clue to the presence of enterovirus D68. Because the patient had respiratory failure, further sequencing was done on the isolate. The isolate was identified as human rhinovirus 36.

2. Rhinovirus, unlike enterovirus, is tropic to the upper and not the lower respiratory tract. However, rarely, it can cause lower respiratory tract disease. Infection with rhinovirus is not associated with acute lung rejection in one case series.


Case # 3. A 30 year old man with well controlled HIV infection on HAART presented with acute rash that involved his bilateral palms and soles as well as acute Bell's palsy. 

Taken from: http://upload.wikimedia.org/wikipedia/commons/2/29/Treponema_pallidum.jpg

1. Bell's palsy occurs in secondary and tertiary forms of syphilis hence, performing a lumbar puncture to rule out neurosyphilis is warranted.

2. This patient had a normal head CT scan and lumbar puncture revealed 0 white cells and normal total protein. The absence of white cells in the CSF can rule out neurosyphilis but a more definitive test (although not standardized) that rules this out is a negative CSF FTA. The latter is usually ordered when the clinical suspicion for neurosyphilis remains in the presence of mild CSF pleocytosis and a negative CSF VDRL.

3. Read more about other unusual manifestations of secondary syphilis (i.e. gastropathy, hepatitis, Bell's palsy, aseptic meningitis ) here.

Tuesday, September 9, 2014

September 9, 2014 Grand Rounds

Case #1. A 70 year old man with relapsed AML undergoing chemotherapy admitted with fever, fatigue, sore throat, and cough; CT scan showed tracheal enhancement and mediastinitis; bronchoscopy showed pseudomembranous lesions; a case of invasive trancheobronchial aspergillosis

 Taken from: http://www.aspergillus.org.uk/secure/image_library/tracheobronch/fig7.jpg

1. Remember the different manifestations of aspergillosis in immunocompromised patients: pulmonary (from acute nodular lung disease to the more indolent necrotizing/cavitary form), tracheobronchitis, disseminated form, and rhinosinusitis. Less common manifestations that are well described in the literature include central nervous system involvement (brain abscess), endophthalmitis, endocarditis, gastrointestinal, or cutaneous lesions.

2. Invasive tracheobronchial aspergillosis (ITBA) is seen in <10% of patients with invasive aspergillosis. It is usually diagnosed late  because it can have normal imaging early in its course. A predisposed patient who comes in with fever, significant cough, and shortness of breath without pneumonia on chest CT scan should alert you to this diagnosis. Bronchoscopy is the best way to look for it.

3. ITBA has 3 forms: ulcerative (seen in AIDS and heart-lung transplant patients), pseudomembranous (seen in patients with hematologic malignancies), and obstructive (mucus plugs are usually seen but no bronchial inflammation is evident). Mixed forms can also be observed in <10% of patients with ITBA.

4.    ITBA is usually associated with a negative blood galactomannan.


Case # 2. A 15 year old girl presented with acute onset back pain and fever secondary to Group A Streptococcus epidural abscess

 http://images.ddccdn.com/images/pills/mtm/Clindamycin%20300%20mg-RAN.jpg

1. Always keep epidural abscess in your differential diagnosis for fever and back pain especially if patients have neurologic deficits. Be aware of the different stages of epidural abscess symptomatology: stage I (back pain, fever, tenderness), stage II (spinal root signs such as radicular pain), stage III (sensory and motor deficits, bladder/bowel dysfunction), and stage IV (paralysis).

2. This patient was treated with both ceftriaxone and clindamycin initially. The basis of combining clindamycin with penicillin in the treatment of Streptococcus pyogenes infection (especially in cases of high burden infection) early in its course is not only to prevent toxin release (in cases of necrotizing fasciitis) but also to counteract the theoretical Eagle effect. The latter is the paradoxical reduction of the bactericidal activity of high dose penicillin in infections with heavy Streptococcus pyogenes burden. The proposed mechanism is the reduced expression of penicillin-binding proteins by bacteria induced to a stationary phase of growth by the heavy bacterial burden. Clindamycin kills these bacteria in the stationary phase as its ability to inhibit bacterial protein synthesis is not dependent on bacterial growth stage or bacterial load.


Case # 3. Update on enterovirus D68

1. Enterovirus D68 was first isolated in 1962 in California. Since then, sporadic outbreaks have been seen. From 2008-2010, outbreaks have been documented in the Netherlands, Japan, China, and the Philippines. It has rarely been reported in the US until last month (read here).

2. Enterovirus D68 manifests almost exclusively as a respiratory illness of varying severity (from mild illness to frank respiratory failure requiring ventilatory support or extacorporeal membrane oxygenation). Rare cases have been associated with neurologic manifestations (e.g. flaccid paralysis and meningoencephalitis).

3. The clinician should be alerted of this entity when a multiplex PCR give out a result "enterovirus/rhinovirus". The virology lab can be called for genotypic identification as this is the only way to diagnose enterovirus D68. 

4. There are no specific treatments available for enterovirus D68 infection.

Tuesday, September 2, 2014

September 2, 2014 Grand Rounds

Case # 1 A 47 year old immunocompetent man with no significant past medical history who presented with  6 weeks of headache, neck pain, and fever secondary to Cryptococcus neoformans infection

1. In immunocompetent patients, Cryptococcus neoformans usually affects the central nervous system causing subacute to chronic meningitis. Patients often present with headache that is repeatedly misdiagnosed as migraine or cluster headache. 

2. Apart from HIV infection and receipt of immunocompromising medications (for transplantation, cancer, or rheumatologic disorders), other well-characterized immunodeficiency states that predispose to cryptococcal infection include CD4 lymphopenia and presence of anti-GM-CSF autoantibodies (read here).

3. Further ID pearls about cryptococcal infection are listed under Case # 1 June 24, 2014.


Case # 2. A 7-day old baby girl who presented with increased sleepiness, poor feeding, thrombocytopenia, and a diffuse macular rash secondary to parvovirus B19 infection


1. Parvovirus B19 causes fifth disease (erythema infectiosum). Another well-characterized but rarer and hence, less recognized illness that is associated with a rash secondary to parvovirus B19 is called papular-purpuric gloves and socks syndrome (PPGSS). PPGSS (see picture) is characterized by symmetrical and well-demarcated erythematous lesions on the hands and feet that end abruptly at the level of the wrist and ankle. It can present with high fever, mucosal lesions, and arthralgia (read here).

2. Other well-known illnesses associated with parvovirus B19 include: symmetric arthritis/arthralgia, transient aplastic crisis, chronic pure red cell aplasia, and non-immune hydrops fetalis. Rare manifestations include: acute hepatitis, fulminant liver failure, immune-complex glomerulonephritis, myocarditis, ITP, and TTP.


Case # 3. A 30 year old woman who is 13 weeks pregnant and who has a h/o splenectomy secondary to hereditary spherocytosis presented with fever and acute-onset watery diarrhea 2 days after eating in a restaurant secondary to Campylobacter jejuni infection (blood and stool culture positive)

1. Campylobacter usually causes a self-limited gastroenteritis and hence, treatment is not usually advised. However, treatment is recommended for those who present with severe disease (i.e. bloody diarrhea, high fever, extraintestinal infection, worsening or relapsing symptoms, or symptoms > 1 week duration) or those at risk for severe disease (e.g. immunocompromised, elderly, and pregnant patients).

2. The prevalence of fluoroquinolone-resistant Campylobacter is rising. In Thailand and Spain, for example, the prevalence is as high as 80%. In the US, fluoroquinolone-resistant Campylobacter has also risen from 0% to 19% between 1989 and 2001. Hence, some authorities advocate a macrolide (azithromycin or erythromycin) as first line agent against this infection.

3. Other antibiotics that can be used against Campylobacter include: aminoglycosides, carbapenem (especially for severely ill patients), clindamycin, tetracyclines, and chloramphenicol. It is inherently resistant to trimethoprim and some beta-lactam antibiotics including penicillin and most cephalosporins.

4. Campylobacter fetus is an uncommon species of Campylobacter that usually affects immunocompromised hosts, including elderly and pregnant women, and causes bacteremia and meningitis.

5. More ID pearls about Campylobacter are listed under Case # 2 July 2, 2014.

Tuesday, August 26, 2014

ID Grand Rounds. August 26, 2014

Case # 1. A 65 year old, CMV D+/R- kidney transplant recipient receiving mycophenolate and prednisone presented with 1 month h/o hematuria and progressive renal failure secondary to adenovirus nephritis.

From: https://www.google.com/search?q=adenovirus+electron+microscopy&source=lnms&tbm=isch&sa=X&ei=RP_8U9GlGsO0yAS5lICQCQ&ved=0CAgQ_AUoAQ&biw=1920&bih=943#facrc=_&imgdii=_&imgrc=jysh9OgcvqH5YM%253A%3BqFxYXFIK5hJFGM%3Bhttp%253A%252F%252Fwww.virology.net%252Fbig_virology%252FEM%252FAdeno-FD.jpg%3Bhttp%253A%252F%252Fwww.virology.net%252Fbig_virology%252FBVDNAadeno.html%3B979%3B964

1. Know the different clinical manifestations of adenovirus infection in immunocompromised patients: pneumonia (including necrotizing pneumonia and diffuse alveolar damage), gastroenteritis, hepatitis, hemorrhagic cystitis, interstitial nephritis, and meningoencephalitis. Among immunocompetent patients, adenovirus infection usually manifests as nonspecific upper respiratory tract illness, gastroenteritis, pharyngo-conjunctival fever, and epidemic keratoconjunctivitis.

2. Kidney transplant recipients who developed adenovirus graft-nephritis had better survival compared to other transplant recipients who developed native-kidney adenovirus nephritis according to one case series.

3. Histopathologic examination of a biopsy specimen is the gold standard for diagnosing invasive adenoviral infection. In situ hybridization is utilized to confirm the presence of the virus in tissues. Cells infected with adenovirus have large nuclei with basophilic inclusions and a thin rim of cytoplasm (so called smudge cells). Granulomatous formation is often observed. Adenovirus PCR can also be used but it should always be correlated with histopathology and with the clinical presentation to distinguish between asymptomatic infection and disease.

4. In immunosuppressed patients, the cornerstone of management for invasive adenovirus infection is supportive care and reduction of immunosuppression (read here). If treatment is desired, cidofovir is likely the best antiviral agent to use. Probenecid is used together with cidofovir to block active renal tubular secretion of cidofovir, thereby, preventing the development of nephrotoxicity. Aggressive hydration with fluid is recommended with cidofovir use.

5. In patients who develop adenovirus nephritis, concurrent use of probenecid is not recommended to ensure increased drug delivery to the site of infection.


Case # 2. A 6 year old child presented with 1 day of fever, diffuse maculopapular rash, and knee pain after returning from a 1 month trip to Puerto Rico a few days prior to admission secondary to chikungunya fever.

From: http://www.cdc.gov/chikungunya/images/maps/CHIK_Americas_Map-081214.jpg

1. Chikungunya ("that which bends up" in Tanzanian), was first described from an outbreak of fever in Tanzania in 1952.

2. It is characterized by fever that lasts for 3-5 days followed 2-5 days later by polyarthralgia (hands > wrists > ankles) that can sometimes be extremely debilitating. A diffuse maculopapular rash (which is pruritic in up to 50%) occurs in 40-75% of patients.  After the acute illness, up to 60% of patients can have persistent joint pains for up to 36 months.

3. The closest differential diagnosis is dengue fever as it is also transmitted by the Aedes mosquito vector. The main difference between dengue and chikungunya fever is that myalgia and polyarthralgia are virtually present in all chikungunya patients while they are uncommon findings in dengue patients. Thrombocytopenia is also more severe in dengue fever.

4. If the illness is suspected early (<5 days), obtaining plasma for viral PCR testing is the best method to diagnose chikungunya fever. Plasma viral-specific IgM and neutralizing antibodies are usually checked after 5 days of illness. Samples should be sent to the state laboratory or the CDC.

5. Outbreaks have traditionally been localized in Africa, Asia, and Europe but in December 2013, for the first time, chikungunya virus was found in the Americas. At present, there is an outbreak of chikungunya fever in the Caribbean. In July 2014, 2 patients from Florida who had not traveled outside of the US were diagnosed with chikungunya fever as reported by the CDC (read here).


Case # 3. A 21 year old woman from India develops fever, myalgia, diarrhea, severe leucopenia/thrombocytopenia, rhabdomyolysis, hepatitis, and multi-organ failure secondary to ciprofloxacin-resistant Salmonella enterica serotype Typhi infection (typhoid fever)

1. Tyhpoid fever can cause bone marrow suppression either by direct infiltration or induction of the macrophage activating system (hemophagocytic syndrome). Salmonella in the bone marrow can also lead to granuloma formation.

2. Alternative antibiotics used for the treatment of ciprofloxacin-resistant Salmonella include: ceftriaxone, azithromycin, or chloramphenicol. Other agents that may be active include imipenem and trimethoprim-sulfamethoxazole.

Tuesday, August 19, 2014

August 19, 2014 Grand Rounds

Case # 1. A 35/F presented with 4 month history of fever, diarrhea, vomiting, 30 pound weight loss, and granulomatous ileitis 

1. Several differential diagnoses were brought up including tuberculosis, histoplasmosis, Crohn's disease, sarcoidosis, and lymphoma. A useful article to review the different causes of granulomatous disease is linked to Case # 3 from June, 17, 2014.

2. It is hard to distinguish Crohn's disease from gastrointestinal tuberculosis especially in areas where the prevalence of both diseases is high. A positive anti-Saccharomyces cerevesiae (ASCA) antibody test is common in patients with Crohn's disease while a positive tuberculin skin test (TST) or interferon gamma release assay can be supportive of tuberculosis. Tissue culture remains the gold standard of diagnosing gastrointestinal tuberculosis.

3. Again, it was emphasized (similar to Case # 3 from June 17, 2014) that multiple tissue biopsies and cultures should be obtained to determine the cause of the granulomatous process. Empiric anti-tuberculous treatment may be warranted in some patients if the index of suspicion for tuberculosis is high.


Case # 2. A 7-week old infant presented with 1 day history of irritability, low grade fever, tachycardia, and localized neck cellulitis and adenitis secondary to group B Streptococcus (GBS)

From: http://www.giglig.com/wp-content/uploads/2011/09/Streptococcus.jpg

1. GBS cellulitis-adenitis syndrome is a rare (34 cases in the literature) but well-described late-onset GBS disease in neonates and infants. The median age of onset is 4.5 weeks. It usually presents as fever, increased irritability, and poor feeding followed by the appearance of lymphadenitis that is usually located in the submandibular region. In >90% of cases, GBS is isolated from the blood or from the lymph node.  


Case # 3. A 58/F presented with acute onset fever, nausea, vomiting, diarrhea, leukocytosis to 44,000, enterocolitis on CT scan, and septic shock several weeks after completing levofloxacin treatment for community acquired pneumonia; stool C. difficile toxin test is negative on two occasions

From: https://ndnr.com/wp-content/uploads/2012/01/10045000_m.jpg

1. The sensitivity of Clostridium difficile toxin enzyme immunoassay (EIA) is 63-94% depending on the the commercial test used (read here). The EIA we use for detecting Clostridium difficile toxin in our hospital is called TECHLAB assay. From the package insert, this test, compared to tissue culture cytotoxicity assay which is the gold standard in diagnosing Clostridium difficile, has a sensitivity of 92.2%, specificity of 100%, negative predictive value of 98.6%, and positive predictive value of 100% (read here).

2. The EIA can have as much as 10-20% false negative rate (read here). Thus, in some rare cases when this test is negative, it may be reasonable to continue treatment for Clostridium difficile. Although, in these cases, one should always look for other competing diagnoses such as ischemic bowel disease and other antibiotic-associated enterocolitis (e.g. Campylobacter, Salmonella).